
Melanotan II
Also known as: MT-II, MTII
Quick summary
Melanotan II is a cyclic, highly potent synthetic analogue of alpha-MSH. Research focus: melanocortin receptor agonism, skin pigmentation and food intake signaling. This page leads with SRP's low-and-slow starting dose.
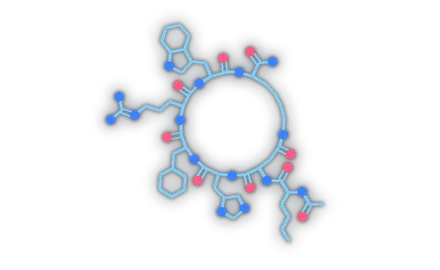
2D structure
Overview
Melanotan II is a cyclic, highly potent synthetic analogue of alpha-MSH. It was developed at the University of Arizona and activates several melanocortin receptors. It shows up in pigmentation, feeding and central melanocortin research.
Looking for research material? Simple Research Peptides lists Melanotan II (10 mg Vial) for laboratory research use.
Mechanism
A cyclic, broadly acting melanocortin agonist (MC1R, MC3R, MC4R and MC5R) that affects pigmentation, appetite and sexual behavior.
Research areas
- melanocortin receptor agonism
- skin pigmentation
- food intake signaling
- central MC4R research
Storage & reconstitution
Supplied as a lyophilized powder; keep sealed, dry and away from light, ideally frozen or refrigerated for long-term holding. Laboratories typically reconstitute with bacteriostatic or sterile water, swirling gently rather than shaking, then hold the solution refrigerated (2–8 °C) and use it within the window set by their own stability protocol.
Recommended starting dose (low and slow)
| Starting dose | A small test amount first: 100-250 mcg daily for days 1-3, 250 mcg test. range starts at 100 mcg. |
|---|---|
| Frequency | Reported schedules: daily during loading, then 1–2x weekly; 250mcg test, 500mcg daily load 1–4wk, then 500mcg weekly-biweekly; Varies by study; 2–3x weekly. Reported schedules vary. |
| Reconstitution | Examples: 10 mg vial + 2 mL bacteriostatic water = 5 mg/mL; 10 mg vial + 2 mL water = 5 mg/mL; 10mg vial + 2mL diluent (as listed). storage note: Reconstituted: refrigerate, used within 4–6 weeks. |
Studied higher doses
Studies have used doses up to the amounts below. Higher doses can be dangerous. Whether a person can reach them safely depends on height, weight, activity level, training and pre-existing conditions. We recommend following the lower starting dose above, and contacting SRP with any questions.
| Highest amount reported in studies | Conflict: allows up to 1,000 mcg (1 mg) per dose; stop at 500 mcg; reference tops at 1 mg; up to 2 mg per injection. Case reports exist of toxicity and melanoma. |
|---|---|
| Step-up schedules reported | Example: 100-250 mcg daily days 1-3, 250-500 mcg days 4-14, 500-1,000 mcg weeks 3-6 (loading), then maintenance 500-1,000 mcg once or twice weekly (or 250-500 mcg weekly). 500 mcg daily for 1-4 weeks, then 500 mcg weekly to every two weeks. |
Route and timing
Route: Subcutaneous injection after reconstitution is the route most often described in research protocols.
Timing: Pending - to be added by SRP
Cycle length and repeat
Pending - to be added by SRP
Half-life
Approximate, for Bobby's review: Not well characterized in published research.
Side effects
Pending - to be added by SRP
Suggested bloodwork and monitoring
Draft, for Bobby's review: CBC and comprehensive metabolic panel (kidney and liver function, electrolytes) before starting and again after a few weeks; blood pressure; a skin and mole check at baseline.
Cautions
Pending - to be added by SRP
Reconstitution calculator
Math aid only. It converts the numbers you enter; it is not dosing advice. For research use only. Prefilled with this page's vial size, reconstitution and low-and-slow starting dose where known; change any value.
Frequently asked questions
What is Melanotan II studied for?
In research it is studied for melanocortin receptor agonism, skin pigmentation and food intake signaling. A cyclic, broadly acting melanocortin agonist (MC1R, MC3R, MC4R and MC5R) that affects pigmentation, appetite and sexual behavior.
How is Melanotan II given in research?
Subcutaneous injection after reconstitution is the route most often described in research protocols. See the dosing frequency block on this page for how often.
What amount should a researcher start with?
This page lists SRP's low-and-slow starting dose in the Recommended starting dose section. Higher amounts that appear in studies are listed separately with their safety context. Start with the lower dose and contact SRP with any questions.
Related peptides
Last updated: October 19, 2026